Chronic Kidney Disease in Cameroon: Drivers, Opportunities and Challenges
Overview
This policy briefing synthesizes key insights from the Cameroon Townhall for Healthcare Professionals meeting held in March 2024, focusing on the theme "Chronic Kidney Disease in Cameroon: An Overview of Drivers, Opportunities and Challenges," presented by Dr. Ronald Gobina, consultant nephrologist at the Buea Regional Hospital.
Context
At least one in ten Cameroonian adults has chronic kidney disease, and the true figure may be higher. Every region now has a haemodialysis centre and dialysis is free, but there are about 30 nephrologists for 30 million people, no kidney biopsy service and no chronic peritoneal dialysis, and many patients stop dialysis within a month.
Key issues
- Rising and poorly understood burden. Diabetes, hypertension, obesity, hepatitis B and HIV drive CKD, while traditional medicines and other local causes are under-studied.
- No kidney biopsy. Diagnoses rest on clinical syndromes, which weakens national data.
- Dialysis access and dropout. About half of those in need get dialysis, up to 84% stop after six or seven sessions, and centres are overloaded or under-used.
- Inefficient spending. Duplicate water treatment rooms, uneven allocation of machines, overpriced kits, and imported normal saline.
- Gaps in training and medicines. No formal dialysis training in nursing schools, and frequent shortages of essential nephrology drugs.
Discussion highlights
- Participants welcomed free dialysis and the start of kidney transplant and paediatric peritoneal dialysis.
- Pathology was described as the main diagnostic gap across specialties.
- Few people are willing to be living kidney donors; awareness campaigns are planned.
- Access to drugs that slow CKD depends on price negotiation and on clinical trials in Africa.
- Herbal medicine was named as a local driver needing research and dialogue with traditional practitioners.
Recommendations
- Screen for CKD early. MINSANTE and regional delegations should screen people with diabetes, hypertension, HIV and hepatitis B using serum creatinine and urine tests, with ultrasound where possible, and link those found to care. First step: build on the World Kidney Day screening model in Buea in other regions.
- Start kidney pathology services. MINSANTE, university hospitals and private investors should set up at least one renal pathology laboratory with immunofluorescence, receiving samples from across the country, and train pathologists in renal pathology.
- Plan dialysis capacity rationally. MINSANTE should allocate machines by patient load, require new brands to use existing water treatment rooms where capacity allows, keep old machines maintained, and review procurement prices of dialysis kits. First step: an audit of capacity and use in every dialysis centre.
- Produce dialysis fluids locally. MINSANTE and industry should support local production of normal saline and peritoneal dialysis solutions, which would also make chronic peritoneal dialysis possible.
- Train the dialysis team. Nursing and technician schools should add dialysis care to their curricula, and nephrology training should expand through twinning with centres abroad, including interventional nephrology. Diaspora professionals can support training of nurses and technicians.
- Address traditional medicine and drug access. MINSANTE's traditional medicine department and the Cameroon Society of Nephrology should open a dialogue on nephrotoxic remedies, and MINSANTE should negotiate prices for drugs that slow CKD and keep essential nephrology drugs and transplant medicines in stock.
Next steps
The town hall planned a survey of members working in kidney care and invited Giveback Project reports. The nephrology society planned documentaries on kidney transplant to encourage donation. A clinical trialist was invited to speak at a later session on making Cameroon a viable trial site. The next session was set for two weeks later.
Conclusion
Cameroon has made real gains in dialysis access, but CKD remains under-recognised and late in diagnosis. Participants agreed that early screening, kidney pathology, rational use of resources and training of the full kidney care team would do the most to slow the epidemic.
Meeting minutes
Agenda
- Welcome and opening remarks by Elvis Ndansi and Dr. Bryan Tegomoh, and reflections from regular participants
- Presentation by Dr. Ronald Gobina on chronic kidney disease in Cameroon
- Reactions from the Chair and Dr. Samuel Ndinjiakat
- Discussion and Q&A moderated by Dr. Bryan Tegomoh
- Closing remarks and summary by the Chair and Elvis Ndansi, final words from the speaker, and next meeting
Opening remarks
- Elvis Ndansi noted that the session now started at 6 p.m. Cameroon time (1 p.m. Eastern Time) after the US change to daylight saving time, which might reduce attendance.
- Dr. Tegomoh described chronic kidney disease (CKD) as a growing silent epidemic linked to Africa's epidemiological transition, with diabetes and hypertension as major risk factors, and raised possible drivers of CKD in young people: diet, substance use, traditional medicines and genetic predisposition. He called for epidemiological surveillance.
- Elvis Ndansi said about 850 million people worldwide have CKD and that about 90% do not know it until late. He noted that Cameroon keeps opening dialysis centres, yet patients still wait for sessions, and raised heat stress as a possible driver.
- Dr. Samuel Ndinjiakat said his centre in Ndop sees many patients with CKD but must refer them because there is no dialysis in the area.
Presentation
1. Definitions and measurement
Dr. Gobina explained that 'kidney function' in nephrology refers to glomerular filtration, usually estimated from creatinine, and that CKD under the KDIGO definition requires either a reduced filtration rate (below 60 ml per minute) or markers of kidney damage such as albuminuria, urine sediment or structural abnormalities. Creatinine depends on muscle mass, and equations not developed with Africans in mind give very different estimates: the proportion of Cameroonians classed as having CKD changed considerably between Cockcroft-Gault, MDRD and CKD-EPI (2021). Whatever the equation, studies show at least one in ten Cameroonian adults has CKD.
2. Burden and drivers
He cited a general population CKD prevalence of about 16% in Africa, from about 6% in North Africa to 19% in West Africa, with Cameroon in the middle, and said these are underestimates. Diabetes and hypertension lead in every study, with obesity, hepatitis B, HIV and, he suggested, parasitic infections. He questioned calling local causes 'non-traditional': in his practice, herbal and traditional medicines bring more people to dialysis than recognised, including a traditional practitioner who needed dialysis because of his own remedies. He said Cameroon must define its own risk factors.
3. Mortality and cost
Hospital studies in Cameroon found very high mortality, with about one in two people with CKD dying, one in four patients starting dialysis dying within the first year (half of them within six months), and worse outcomes where hypertension and diabetes coexist. He cited a US dollar estimate of about $4,600 a year in out of pocket dialysis costs, against a minimum wage that used to be around 34,000 FCFA a month, and said families lose businesses and livelihoods.
4. No kidney biopsy
Kidney biopsy, which needs light microscopy plus immunofluorescence and a trained renal pathologist, was described as nearly non-existent in Cameroon, so diagnoses such as chronic glomerulonephritis are clinical only and Cameroonian data carry little weight. A systematic review covering 34 years found only 13 African countries that had done at least 50 kidney biopsies, about 70% of the data from North Africa.
5. Limited treatment
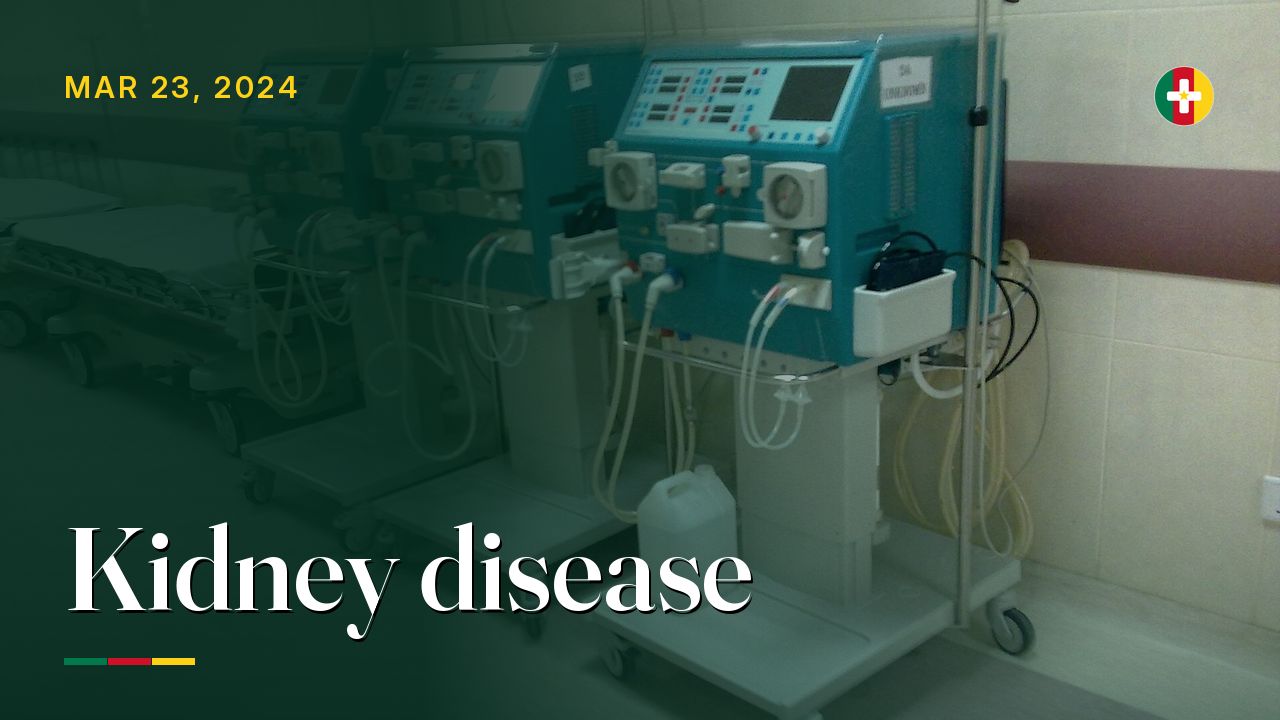
Cameroon has about 30 nephrologists for 30 million people. Haemodialysis is offered twice a week rather than three times, and in overloaded centres patients wait days for shortened sessions. He said 51% of those who need dialysis get it and up to 84% stop after six or seven sessions, mostly from financial exhaustion, with over 90% of these presumed dead. Arteriovenous fistula surgery is available only in Yaoundé, Douala, Garoua and Buea, and fistula imaging only recently in Yaoundé. Chronic peritoneal dialysis is absent, and kidney transplant has only just started.
6. Policy progress
Regional haemodialysis centres were ordered from 2007, and with Bafoussam and another regional centre opening the year before, every region now has one; Laquintinie Hospital in Douala opened a centre to relieve congestion. A session costs about 70,000 FCFA, of which patients paid 5,000 FCFA until the government made dialysis free apart from a 15,000 FCFA registration fee. He commended the government and the Yaoundé General Hospital, whose director started kidney transplants with a visiting team from Geneva.
7. Waste and rationality
He said new machine brands insisted on their own water treatment rooms, leaving centres with duplicate systems and idle older machines, and that the military hospital in Yaoundé once inaugurated machines without a water treatment room or consumables. Machines were allocated unevenly, so some centres work four half days a week while others run around the clock. He said procurement rules (the public procurement system) lead to dialysis kits bought at two to three times their market price, and that normal saline used in dialysis is imported although it could be produced locally.
8. Opportunities
He called for data and research to describe Cameroon's own CKD, a private renal pathology laboratory, private dialysis centres (80% of South Africa's are private), twinning for nephrology training, interventional nephrology, psychosocial and dietary support, and a nephrology pharmacy that never runs out of essential drugs. He praised donors who sponsor individual children on dialysis, and asked donors who once paid for single sessions to fund lasting support such as vascular access or income for one patient now that dialysis is free. He estimated the true prevalence could be two or three in ten adults.
Discussion and Q&A
- The Chair (comment) He said the equations used were developed with few Africans, so Cameroon must produce its own research. He said pathology is the biggest gap in care, from immunohistochemistry for breast cancer to immunofluorescence for kidney disease: 'no tissue, no issue'.
- Dr. Samuel Ndinjiakat: what can the diaspora do now, and is there a training curriculum for nephrologists and for support staff such as dialysis nurses and technicians? Dr. Gobina said the head nurse of the Buea dialysis centre had studied this for her master's degree and found that nursing schools include no formal dialysis training. Nephrology training opened around 2012 and produces two or three nephrologists a year; there were about five nephrologists 15 years earlier and at least six are in training in Yaoundé. Few nephrologists have left the country. Elvis Ndansi announced a survey of town hall members working in CKD and invited reports under the Giveback Project.
- A medical student in China: is kidney transplant now a reality in Cameroon, and is there reason for optimism? Several more patients had been transplanted at the Yaoundé General Hospital, with visiting teams (with partners in Geneva) still transferring skills. Transplants are living donor, from family members, and were said to be free for now, but few Cameroonians are willing to donate, so the nephrology society plans documentaries on successful cases. He was optimistic: after a four week exposure abroad he started acute peritoneal dialysis for children in Buea in May 2023 and now receives referrals from across the country, and he expected kidney biopsy and scaled up CKD screening soon.
- A critical care clinician in the US: how are acute kidney injury and children with kidney failure managed, and why do children reach dialysis? There is no chronic peritoneal dialysis in Cameroon because the solutions must be imported. For acute cases he uses a locally mixed solution (Ringer's lactate with 50% glucose) for children under five, as there are no paediatric haemodialysis lines; larger children go on adult haemodialysis under close watch. He said 15 to 20% of patients on chronic dialysis at one point were children, many after untreated nephrotic syndrome that responds to treatment within four weeks, or from traditional remedies. Childhood polycystic disease is rarely seen because affected infants die early.
- Elvis Ndansi: are drugs that slow CKD progression, such as dapagliflozin, available, and could prices be negotiated? Elvis Ndansi disclosed that he is a senior vice president at a company working on CKD and said a pharmaceutical executive had told him Africa was not their market. Dr. Gobina said price negotiation and clinical trials are the routes to access, citing how erythropoietin prices fell as use grew, and said trials should include Africans in Africa, not only African Americans. He also mentioned handheld ultrasound devices for screening.
- Dr. Tegomoh: what methods work for population screening in rural settings? Population based studies are the most useful. Screening should combine serum creatinine with urine markers; in Buea, people with any abnormal marker were offered a free kidney ultrasound. Over 500 people were screened in three days, and many changed their habits afterwards. He said point of care creatinine and ultrasound could bring screening to communities.
- The Chair: how can pathology and biopsy capacity be built, and are post-transplant medicines (tacrolimus, cyclosporine, mycophenolate) sustainable? Dr. Gobina said nephrologists can do and some can read kidney biopsies, but a pathologist is needed to cut and stain, and a private laboratory receiving samples from the whole country could be viable. The Yaoundé General Hospital pharmacy had stocked transplant drugs and could measure drug levels. He described his unsuccessful attempts to get pharmacies to stock nephrology drugs and frequent national shortages of prednisolone. The critical care clinician said lung biopsy depends first on equipment (bronchoscopy, EBUS), and the Chair called for interventional training across specialties.
- A nephrologist at the Yaoundé Central Hospital (comment) The nephrologist said many nephrologists are trained to read kidney biopsies, but few pathologists take up renal pathology because it is slow, technically demanding and poorly paid, and stains are hard to obtain. The transplant programme includes Cameroonian vascular surgeons and urologists who train in Geneva, and she expected it to become independent.
- A clinical trialist (comment) The participant said a sponsor had been unable to run a kidney trial in Cameroon for lack of pathology and biopsy, and that Cameroon is classed in red, unable to host studies, by companies such as Roche and Merck. Elvis Ndansi said disease burden is only one criterion for trial sites, with laboratories, research nurses and pharmacists and site accreditation also required, and urged Cameroonian researchers to work in coalitions rather than silos.
Calls to action and closing
- The Chair said the government had invested in dialysis in all 10 regions and was moving to transplant, but diagnosis depends on pathology, and called for training nurses and technicians rather than proliferating medical schools.
- Elvis Ndansi summarised the drivers: a projected 46% rise in diabetes by 2045, hypertension in about one in three adults worldwide, hepatitis, HIV, obesity and traditional medicines. He proposed that the Cameroon Society of Nephrology engage the Ministry's traditional medicine department on the harms of herbal concoctions.
- Dr. Gobina thanked participants and said he had seen potential partners across fields.
Next meeting
In two weeks, at 6 p.m. Cameroon time (1 p.m. Eastern Time).
Submitted by the Co-Moderators, Cameroon Town Hall for Healthcare Professionals.